Tesamorelin is a growth hormone-releasing factor analog with a defined clinical evidence base in adults with HIV-associated lipodystrophy. That specific population and endpoint context is essential: the evidence should not be generalized into a broad consumer weight-loss claim.
Key takeaways
- Pivotal studies measured visceral adipose tissue in adults with HIV-associated abdominal fat accumulation.
- The FDA label states that the approved product is not indicated for weight-loss management.
- Approved-product evidence does not establish equivalence for an independently supplied research material.
The biological and clinical context
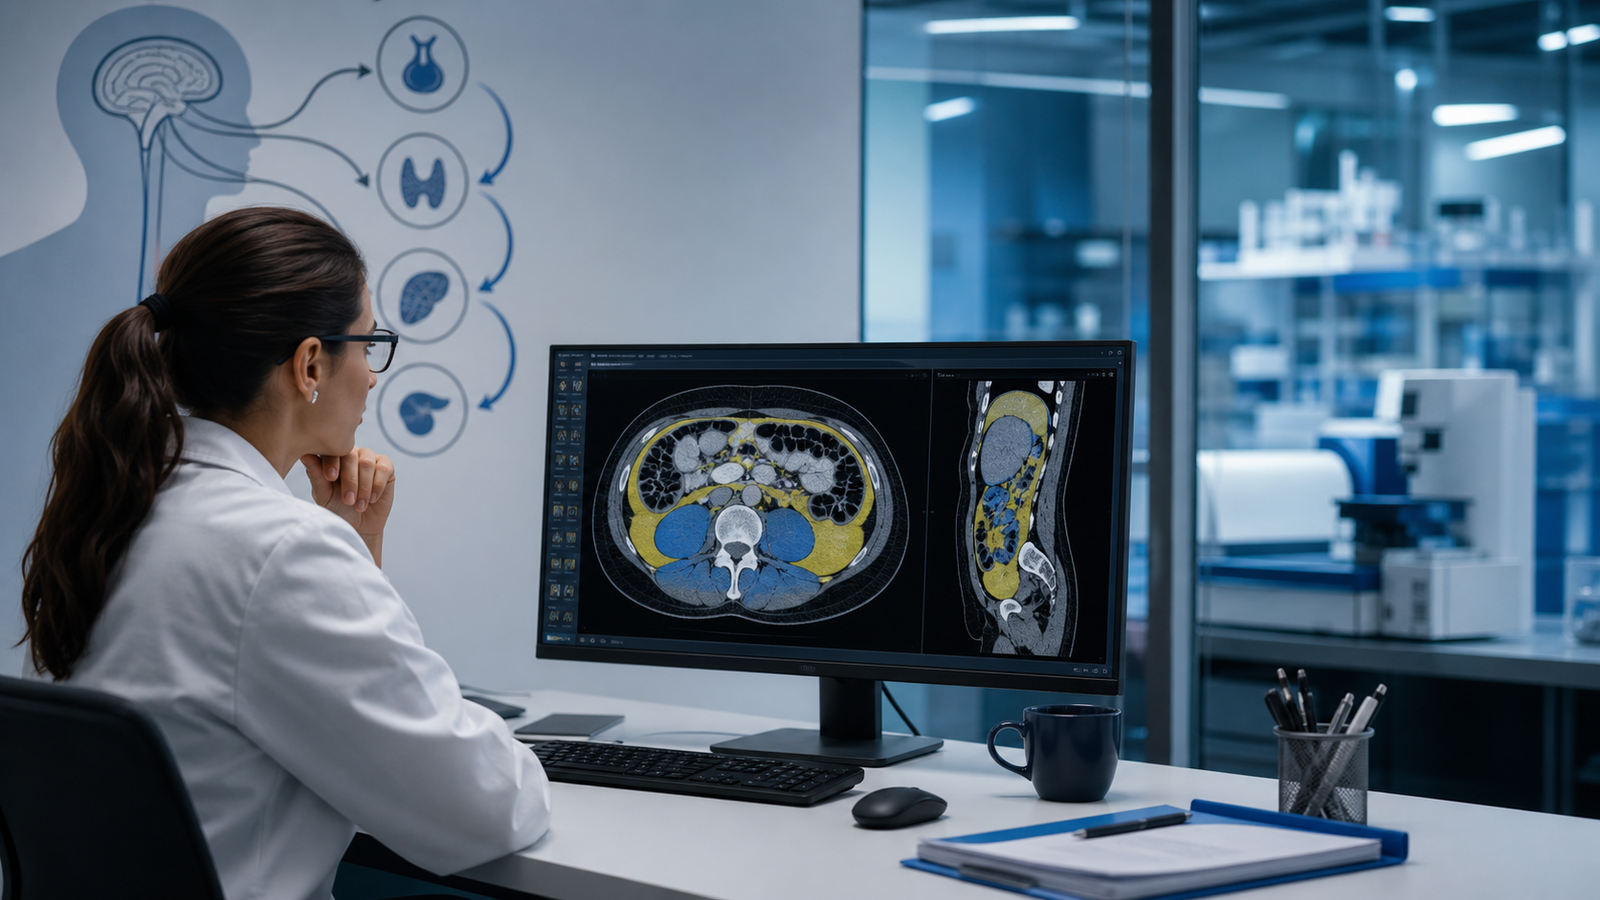
Tesamorelin is an analog of growth hormone-releasing factor. In the studied setting it stimulates pituitary growth-hormone release and increases IGF-1 signaling. The relevant trials enrolled people living with HIV who had excess abdominal fat in the context of antiretroviral therapy.
That context matters because HIV-associated lipodystrophy is not interchangeable with general obesity, and visceral adipose tissue measured by imaging is not the same endpoint as overall weight loss.
What the 12-month randomized study found
A 404-participant randomized placebo-controlled study used visceral adipose tissue as its primary endpoint. The investigators reported a reduction in visceral fat during the initial randomized phase and persistence among participants who continued treatment. Improvements were lost after switching from tesamorelin to placebo, which helps clarify the dependence of the observed effect on continued exposure in that protocol.
A smaller randomized study also assessed liver fat and visceral adipose tissue. Its results were exploratory for liver-related outcomes and should not be converted into an approved liver-disease indication.
Label boundaries that belong in every summary
The 2025 EGRIFTA WR label identifies a specific approved formulation and indication. It also notes that long-term cardiovascular safety has not been established and that the product is not indicated for weight-loss management. Those limitations are part of the evidence, not optional fine print.
Sources & editorial method
The editorial workflow starts with linked peer-reviewed papers, trial registries or regulatory records; extracts the population or model, endpoints, numerical results and limitations; and separates the studied intervention from catalog material. AI-assisted drafting was used to structure the first version. Claims, figures, evidence labels and limitations were checked against the linked records in the site editorial workflow. This is not independent peer review.
3 linked records are listed in the references below. Read the editorial and AI-assistance policy.
How to interpret this article
Source-checked against the linked primary or authoritative records on 2026-08-27. This is an evidence summary, not independent peer review, medical advice or validation of a catalog lot.
Research-use boundary: Catalog materials discussed on this website are for laboratory research, development and manufacturing use only, not for human or veterinary use. This content is not medical advice and does not provide administration instructions.
Primary records and authoritative sources
- Effects of tesamorelin, a growth hormone-releasing factor, in HIV-infected patients with abdominal fat accumulation: a randomized placebo-controlled trial with a safety extensionFalutz J, et al. Journal of Acquired Immune Deficiency Syndromes. PMID 20101189 · DOI 10.1097/QAI.0b013e3181cbdaff
- Randomized trial of visceral and liver fat outcomesExploratory liver-fat evidence; PMID 25038357.
- EGRIFTA WR (tesamorelin) prescribing informationU.S. Food and Drug Administration. 2025 labeling record for BLA 022505.
Continue with structured records
Move from this editorial analysis to the product identity, filtered evidence and controlled terminology behind it.